
Dialysis services across Kenya are facing a looming collapse following widespread claim rejections, delayed payments, and administrative bottlenecks under the Social Health Authority (SHA), raising alarm among healthcare providers and putting thousands of patients at risk.
The Kenya Renal Association has warned of a healthcare system under strain, cautioning that unless urgent reforms are implemented, the country could witness a breakdown in life-saving dialysis services.
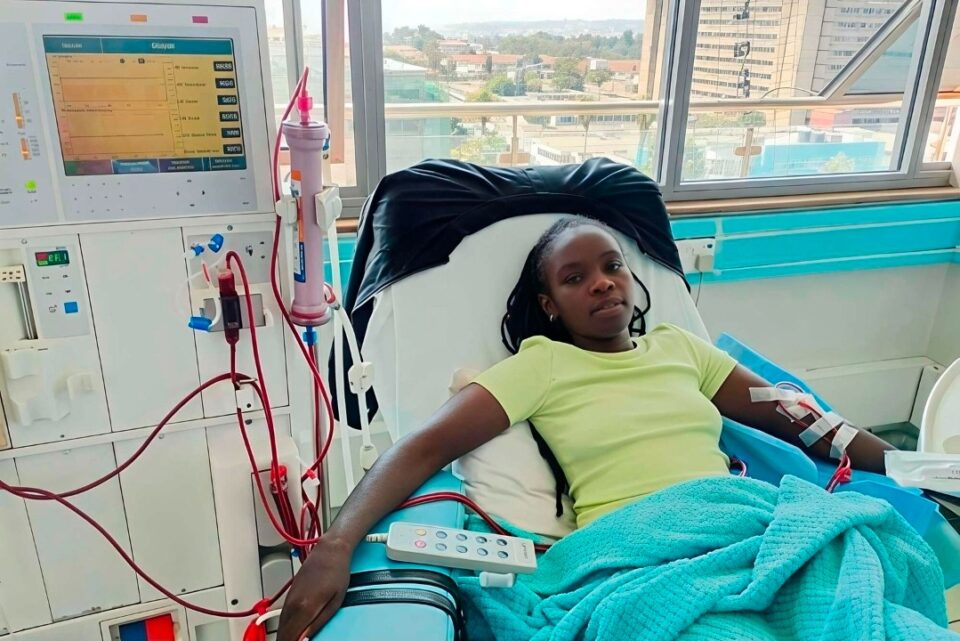
At the centre of the crisis are more than 7,000 patients who depend on dialysis to survive. For individuals with kidney failure, dialysis is not optional—it is a critical, ongoing treatment typically required two to three times a week. Missing even a few sessions can trigger life-threatening complications, including fluid overload, electrolyte imbalance, and death.
“This is not elective care—it is lifeline medicine,” said the association’s president, Dr Jonathan Wala.
Healthcare providers blame systemic failures within the SHA claims processing framework. Claims submitted for reimbursement are frequently rejected without clear, specific, or actionable explanations. In many cases, providers receive generic or automated responses that fail to indicate what went wrong or how errors can be corrected.
This lack of transparency has created a paralysing cycle where providers are unable to resubmit or appeal claims effectively, leaving them unpaid for services already rendered. As a result, facilities are increasingly strained financially even as they continue to offer essential care.
Experts say a critical distinction must be made between administrative and clinical claim rejections—an issue now central to the dispute.
Administrative rejections typically involve paperwork issues such as late submissions, coding errors, or incomplete fields. Clinical rejections, on the other hand, relate to patient eligibility, benefit coverage, or lack of pre-authorisation.
Stakeholders argue that administrative errors should never invalidate legitimate medical claims. Increasingly, providers maintain that no dialysis session that was medically necessary and duly provided should go unpaid due to technicalities.
Under this principle, SHA remains both legally and morally responsible for payment where patients were eligible and treatment was necessary, even if documentation errors occurred.
The Kenya Renal Association warns that current claims practices may violate provisions of the Constitution of Kenya and the Fair Administrative Action Act, which guarantee the right to fair administrative action. These laws require public bodies to provide clear, written reasons for their decisions and allow affected parties an opportunity to correct errors or appeal.
“Providers cannot correct errors if they are not clearly defined,” Dr Wala noted, adding that the absence of a structured appeals framework worsens the problem.
Beyond legal concerns, the crisis has raised ethical questions about who should bear the financial burden when claims are rejected.
In principle, SHA is the primary payer for dialysis services where patients are eligible and treatment is medically necessary. Patients may only be held financially responsible in limited circumstances, such as ineligibility, seeking services outside the benefit package, or non-disclosure.
However, the current reality is different. Providers are increasingly absorbing the cost of rejected claims, effectively subsidising the healthcare system. Experts warn this situation is financially unsustainable, legally challengeable, and systemically dangerous.
“It is both unethical and legally questionable to transfer administrative failures to the patient,” stakeholders note, cautioning against passing costs onto vulnerable patients who have no alternative but to continue treatment.
Financial pressures on dialysis providers are intensifying. Facilities are reimbursed KSh10,650 per session, but a newly introduced two percent deduction—combined with delayed payments and rejected claims—has eroded already thin margins.
Many providers are now struggling to maintain operations. Cash flow constraints have made it difficult to procure essential consumables such as dialysis filters, tubing, and fluids. Staff retention is also becoming a concern as facilities grapple with rising operational costs and uncertain revenue.
If the situation persists, providers warn they may be forced to scale down services or exit the market altogether.
Such an outcome would have severe consequences for Kenya’s healthcare system. The potential collapse of private dialysis services would shift the burden onto public hospitals, many of which are already operating at or beyond capacity.
An influx of patients into public facilities could overwhelm resources, leading to longer waiting times, reduced quality of care, and increased mortality rates.
Stakeholders caution that this is not merely a provider-level issue but a systemic risk with national implications.
“This is a system-level failure in the making,” the association warns.
To avert the crisis, healthcare providers are advocating for immediate and long-term reforms.
Key recommendations include requiring SHA to provide detailed, claim-specific reasons for all rejections and introducing a structured correction window before claims are denied outright. There are also calls to fast-track payments for verified claims and settle outstanding obligations.
Transparency is another major demand. Stakeholders want clear claims submission guidelines, standardised rejection criteria, and a functional appeals framework.
The controversial two percent deduction has also come under scrutiny, with providers urging its suspension pending broader stakeholder consultations and regulatory clarity.
In the meantime, providers are being encouraged to adopt more aggressive recovery strategies to protect their financial viability. This includes classifying rejected claims as administrative or clinical, correcting and resubmitting them within timelines, and escalating disputes through formal appeals.
Providers are also advised to document all rejected claims and aggregate financial losses to strengthen engagement with policymakers and regulators.
At the institutional level, some facilities are considering “protected services” policies to ensure dialysis treatment continues uninterrupted, even amid payment uncertainties. However, experts warn that such measures are not sustainable without systemic reforms.
Kenya has made significant progress in expanding access to dialysis services over the past decade, improving survival rates and quality of life for thousands of patients. But those gains are now under threat.
“A fair, transparent, and functional claims system is not optional—it is essential for survival,” the Kenya Renal Association concludes.
Failure to act, Dr Wala warns, will not only destabilise healthcare providers but could ultimately cost lives, reversing years of progress in the fight against kidney disease.
previous post
